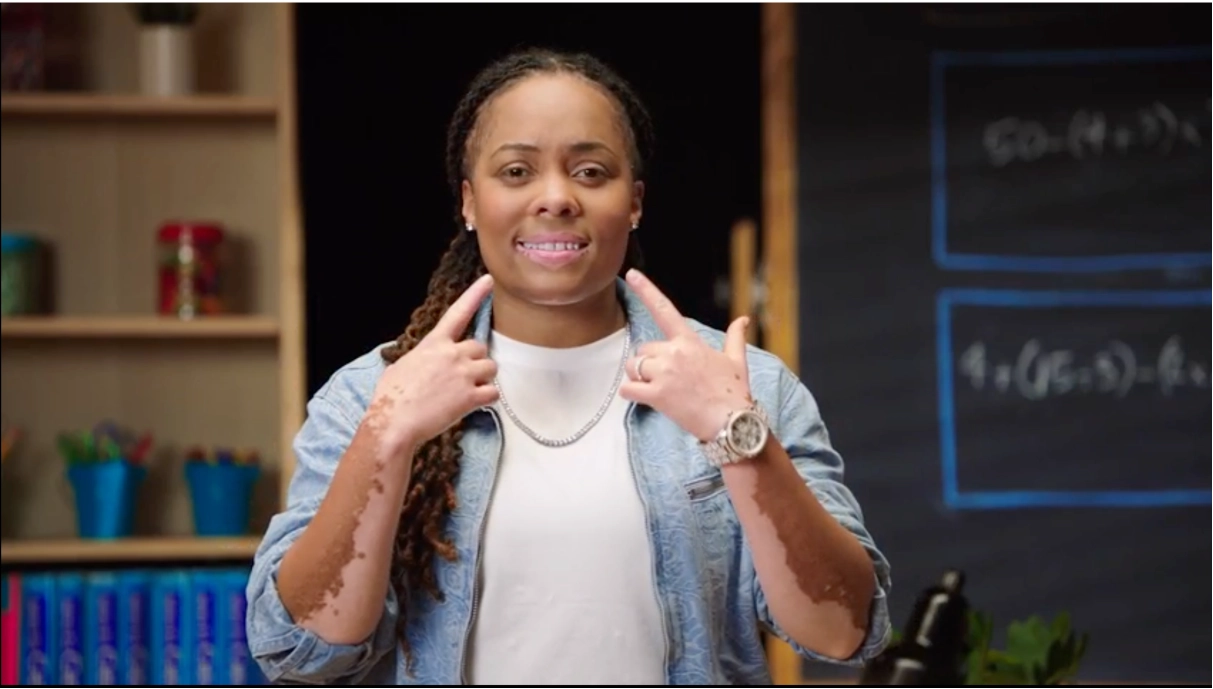OPZELURA is indicated for the topical treatment of nonsegmental vitiligo in adult and pediatric patients 12 years of age and older.

Limitations of Use: Use of OPZELURA in combination with therapeutic biologics, other JAK inhibitors, or potent immunosuppressants such as azathioprine or cyclosporine is not recommended.

TIFFANIE:
REAL OPZELURA PATIENT

Person applying opzelura cream to an area of skin affected by nonsegmental vitiligo. Person applying opzelura cream to an area of skin affected by nonsegmental vitiligo.

WHAT PATIENTS SHOULD KNOW FOR THEIR TREATMENT JOURNEY

Success can start with you. When treating nonsegmental vitiligo, it is important that your patients understand the time to repigmentation varies and each person’s progress with OPZELURA could be different. The following checklist may help with setting patient expectations—BRING IT ON!

Image

ON THE PATH: Repigmentation takes time1

Image

ON SKIN: Time to repigmentation varies depending on body location1

Image

ON REPEAT: Adherence is key: 2X daily application2

Image

ON SCHEDULE: Remember to schedule a follow-up visit2,3

HELPING PATIENTS
STAY ON TRACK

HELPING PATIENTS
STAY ON TRACK

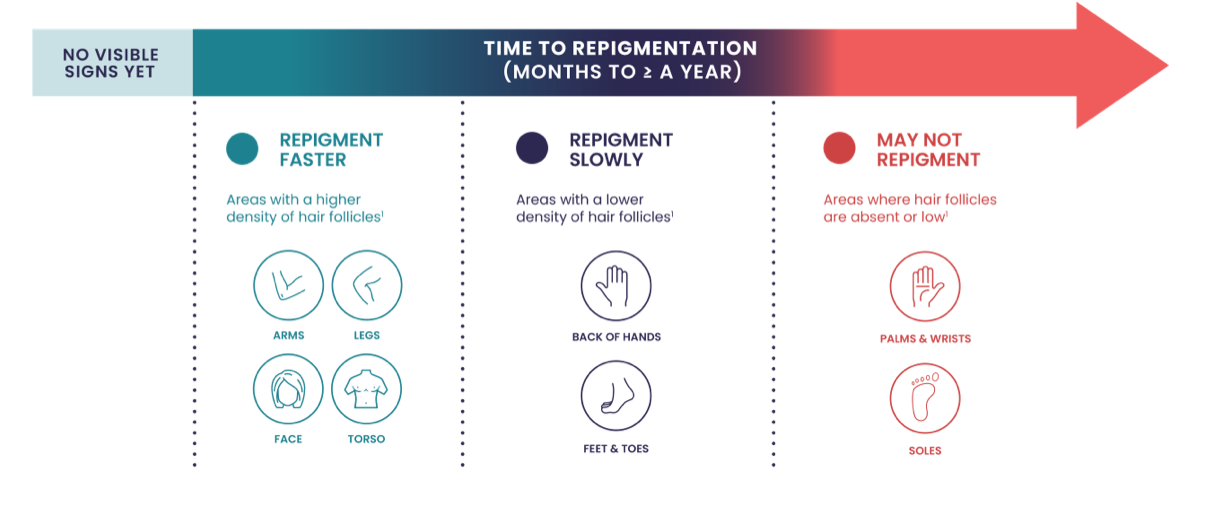
UNDERSTANDING TIME TO REPIGMENTATION

HAIR FOLLICLES PLAY AN IMPORTANT ROLE IN REPIGMENTATION1

Hair follicles are an important source of melanocyte precursors. Melanocytes regenerate in the hair follicle and migrate outwards into the epidermis.1

Image
Time to repigmentation chart. Repigment faster: arms, legs, face, and torso. Repigment slowly: Back of hands and feet and toes. May not repigment: palms and wrists and soles.
Image
Time to repigmentation chart. Repigment faster: arms, legs, face, and torso. Repigment slowly: Back of hands and feet and toes. May not repigment: palms and wrists and soles.
Image

ACRAL (PERIPHERAL) AREAS often have fewer hair follicles.4

Areas with white TERMINAL hair (leukotrichia) are unlikely to repigment.1


PATTERNS OF REPIGMENTATION

Teach patients to look for signs of repigmentation. Repigmentation may occur in one of multiple patterns, including1:

Image
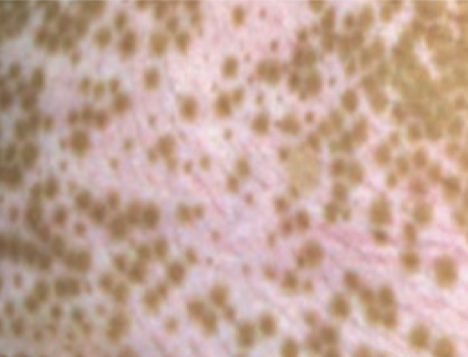
Perifollicular pattern

Perifollicular1,5

The most common pattern is the perifollicular pattern, which appears as small, round, repigmented areas around the hair follicles.

Image
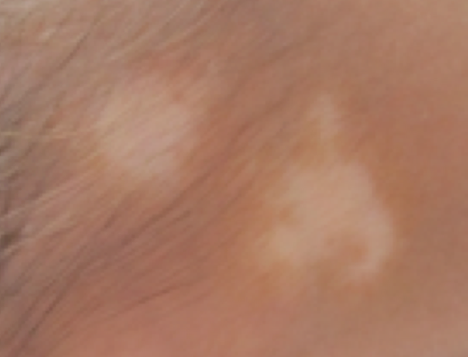
Marginal pattern

Marginal1,6

The marginal pattern appears as a repigmented rim at the lesion borders.

Combined1

In some patients, there can be both perifollicular and marginal repigmentation within the same lesion.

TIFFANIE’S REPIGMENTATION JOURNEY

TIFFANIE’S REPIGMENTATION JOURNEY

Tiffanie was diagnosed with nonsegmental vitiligo at age 7. Despite years of working towards self-acceptance, the decision to pursue repigmentation was not easy. Hear how she drew on resilience instilled by her grandmother, gained confidence to start treatment with OPZELURA, and founded the I AM GREAT MOVEMENT.

TIFFANIE’S JOURNEY

Results may vary.

Tiffanie was compensated for her participation.

REMEMBER: Melanocytes regenerate slowly and migrate over time.1

In addition, each patient's experience will be different. Time to repigmentation may vary between patients and between lesions for a single patient, depending on location on the body.1,7

DOSING INFO FOR OPZELURA2

Review topical dosing information
and how to calculate BSA.

VIEW DOSING

RESOURCES FOR YOU AND YOUR PATIENTS

Support patient education and adherence.

SEE RESOURCES

Important Safety Information and indication


INDICATION

OPZELURA is indicated for the topical treatment of nonsegmental vitiligo in adult and pediatric patients 12 years of age and older.

Limitations of Use: Use of OPZELURA in combination with therapeutic biologics, other JAK inhibitors, or potent immunosuppressants such as azathioprine or cyclosporine is not recommended.

IMPORTANT SAFETY INFORMATION

SERIOUS INFECTIONS
Patients treated with oral Janus kinase (JAK) inhibitors for inflammatory conditions are at risk for serious infections that may lead to hospitalization or death. These include:
  • Active tuberculosis, which may present with pulmonary or extrapulmonary disease.
  • Invasive fungal infections, including cryptococcosis and pneumocystosis.
  • Other bacterial or viral infections, including herpes zoster, due to opportunistic pathogens.
Avoid use in patients with an active, serious infection. If a serious infection develops, stop OPZELURA until the infection is controlled. Carefully consider the benefits and risks of treatment prior to use in patients with chronic or recurrent infection. Closely monitor patients for the development of signs of infection during and after treatment with OPZELURA.

Serious lower respiratory tract infections were reported in the clinical development program with topical ruxolitinib.

No cases of active tuberculosis (TB) were reported in clinical trials with OPZELURA; however, cases were reported in clinical trials of oral JAK inhibitors to treat inflammatory conditions. Consider evaluating patients for latent and active TB infection prior to treatment. Monitor patients for the development of signs and symptoms of TB.

Viral reactivation, including cases of herpes virus reactivation, were reported in clinical trials with JAK inhibitors used to treat inflammatory conditions including OPZELURA. If a patient develops herpes zoster, consider interrupting OPZELURA treatment until the episode resolves.

Hepatitis B viral load (HBV-DNA titer) increases, with or without associated elevations in alanine aminotransferase and aspartate aminotransferase, have been reported in patients with chronic HBV infections taking oral ruxolitinib. OPZELURA is not recommended in patients with active hepatitis B or hepatitis C.

POST-MARKETING SAFETY

In a large randomized postmarketing safety study of rheumatoid arthritis (RA) patients 50 years and older with at least one cardiovascular risk factor, the following were higher with an oral JAK inhibitor than with a tumor necrosis factor (TNF) blocker:

all-cause mortality, major adverse cardiovascular events (defined as cardiovascular death, myocardial infarction, and stroke), thrombosis, malignancies (excluding non-melanoma skin cancer [NMSC]).

Consider the benefits and risks prior to initiating or continuing therapy with OPZELURA. Discontinue OPZELURA in patients who have experienced a myocardial infarction or stroke.

MALIGNANCIES

Malignancies were reported in patients treated with OPZELURA. Lymphoma and other malignancies have been observed in patients receiving JAK inhibitors used to treat inflammatory conditions. Patients who are current or past smokers are at increased risk. Inform patients about the symptoms of serious cardiovascular events and the steps to take if they occur.

Consider the benefits and risks prior to initiating therapy with OPZELURA, particularly in patients:

  • with a known malignancy (other than successfully treated non-melanoma skin cancers),
  • who develop a malignancy when on treatment,
  • with cardiovascular risk factors and
  • who are current or past smokers.

Non-melanoma skin cancers, including basal cell and squamous cell carcinoma, have occurred in patients treated with OPZELURA. Perform periodic skin examinations during OPZELURA treatment. Limit exposure to sunlight and UV light with protective clothing and broad-spectrum sunscreen.

THROMBOSIS
Thromboembolic events were observed in trials with OPZELURA. Thrombosis, including pulmonary embolism (PE), deep venous thrombosis (DVT), and arterial thrombosis have been reported in patients receiving JAK inhibitors used to treat inflammatory conditions. Many of these adverse reactions were serious, and some resulted in death. Avoid OPZELURA in patients at risk. If symptoms of thrombosis occur, discontinue OPZELURA and treat appropriately.
CYTOPENIAS

Thrombocytopenia, anemia, neutropenia, lymphopenia, and leukopenia were reported in the clinical trials with OPZELURA. Consider the benefits and risks for patients who have a known history of these events prior to initiating therapy. Perform CBC monitoring as clinically indicated. Discontinue OPZELURA if symptoms associated with clinically significant decreases in laboratory values occur.

POTENTIAL RISKS RELATED TO JAK INHIBITION

Treatment with oral ruxolitinib has been associated with increases in lipid parameters including total cholesterol, low-density lipoprotein (LDL) cholesterol, and triglycerides, as well as hypoglycemia in patients with diabetes.

ADVERSE REACTIONS

In nonsegmental vitiligo, the most common adverse reactions (≥1%) are application site acne, application site pruritus, nasopharyngitis, headache, urinary tract infection, application site erythema, and pyrexia.

PREGNANCY REGISTRY

There is a registry that monitors pregnancy outcomes in persons exposed to OPZELURA during pregnancy. Pregnant persons exposed to OPZELURA and healthcare providers should report OPZELURA exposure by calling 1-855-463-3463 or visiting www.opzelura.pregnancy.incyte.com.

LACTATION

Advise women not to breastfeed during treatment with OPZELURA and for approximately four weeks after the last dose (approximately 5-6 elimination half-lives).


Please see Full Prescribing Information, including Boxed Warning, and Medication Guide for OPZELURA.

Indication

OPZELURA is indicated for the topical treatment of nonsegmental vitiligo in adult and pediatric patients 12

Important Safety Information

Important Safety Information and indication

Serious Infections

Patients treated with oral Janus kinase (JAK) inhibitors for inflammatory conditions are at risk for serious infections that may lead to hospitalization or death. These include:

Patients treated with oral Janus kinase (JAK) inhibitors for inflammatory conditions are at risk for serious infections that may lead to hospitalization or death. These include:

References: 1. Birlea SA, Goldstein NB, Norris DA. Repigmentation through melanocyte regeneration in vitiligo. Dermatol Clin. 2017;35(2):205-218. doi:10.1016/j.det.2016.11.015 2. OPZELURA Prescribing Information. Wilmington, DE: Incyte Corporation. 3. Van Geel N, Speeckaert R, Taïeb A, et al. Worldwide expert recommendations for the diagnosis and management of vitiligo: position statement from the International Vitiligo Task Force part 1: towards a new management algorithm. J Eur Acad Dermatol Venereol. 2023;37(11):2173-2184. doi:10.1111/ jdv.19451 4. Esmat SM, El-Tawdy AM, Hafez GA, et al. Acral lesions of vitiligo: why are they resistant to photochemotherapy? J Eur Acad Dermatol Venereol. 2012;26(9):1097-1104. doi:10.1111/j.1468-3083.2011.04215.x 5. Birlea SA, Costin G-E, Roop DR, Norris DA. Trends in regenerative medicine: repigmentation in vitiligo through melanocyte stem cell mobilization. Med Res Rev. 2016;37(4):907-935. doi:10.1002/med.21426 6. Yang K, Xiong X, Pallavi G, et al. The early repigmentation pattern of vitiligo is related to the source of melanocytes and by the choice of therapy: a retrospective cohort study. Int J Dermatol. 2018;57(3):324-331. doi:10.1111/ijd.13878 7. Kanwar AJ, Mahajan R, Parsad D. Low-dose oral mini-pulse dexamethasone therapy in progressive unstable vitiligo. J Cutan Med Surg. 2013;17(4):259-268. doi:10.2310/7750.2013.12053